 English
 Français
 Español
 Deutsch
 Italiano
 العربية








Imaging itself is not the endpoint. What matters is whether the information obtained from imaging leads to effective procedural optimization.
A technically successful image acquisition provides little benefit if important findings do not translate into changes in lesion preparation, stent sizing, expansion, lesion coverage, or correction of procedural complications.
Where Does Intracoronary Imaging Add the Most Value?
Acute Coronary Syndrome
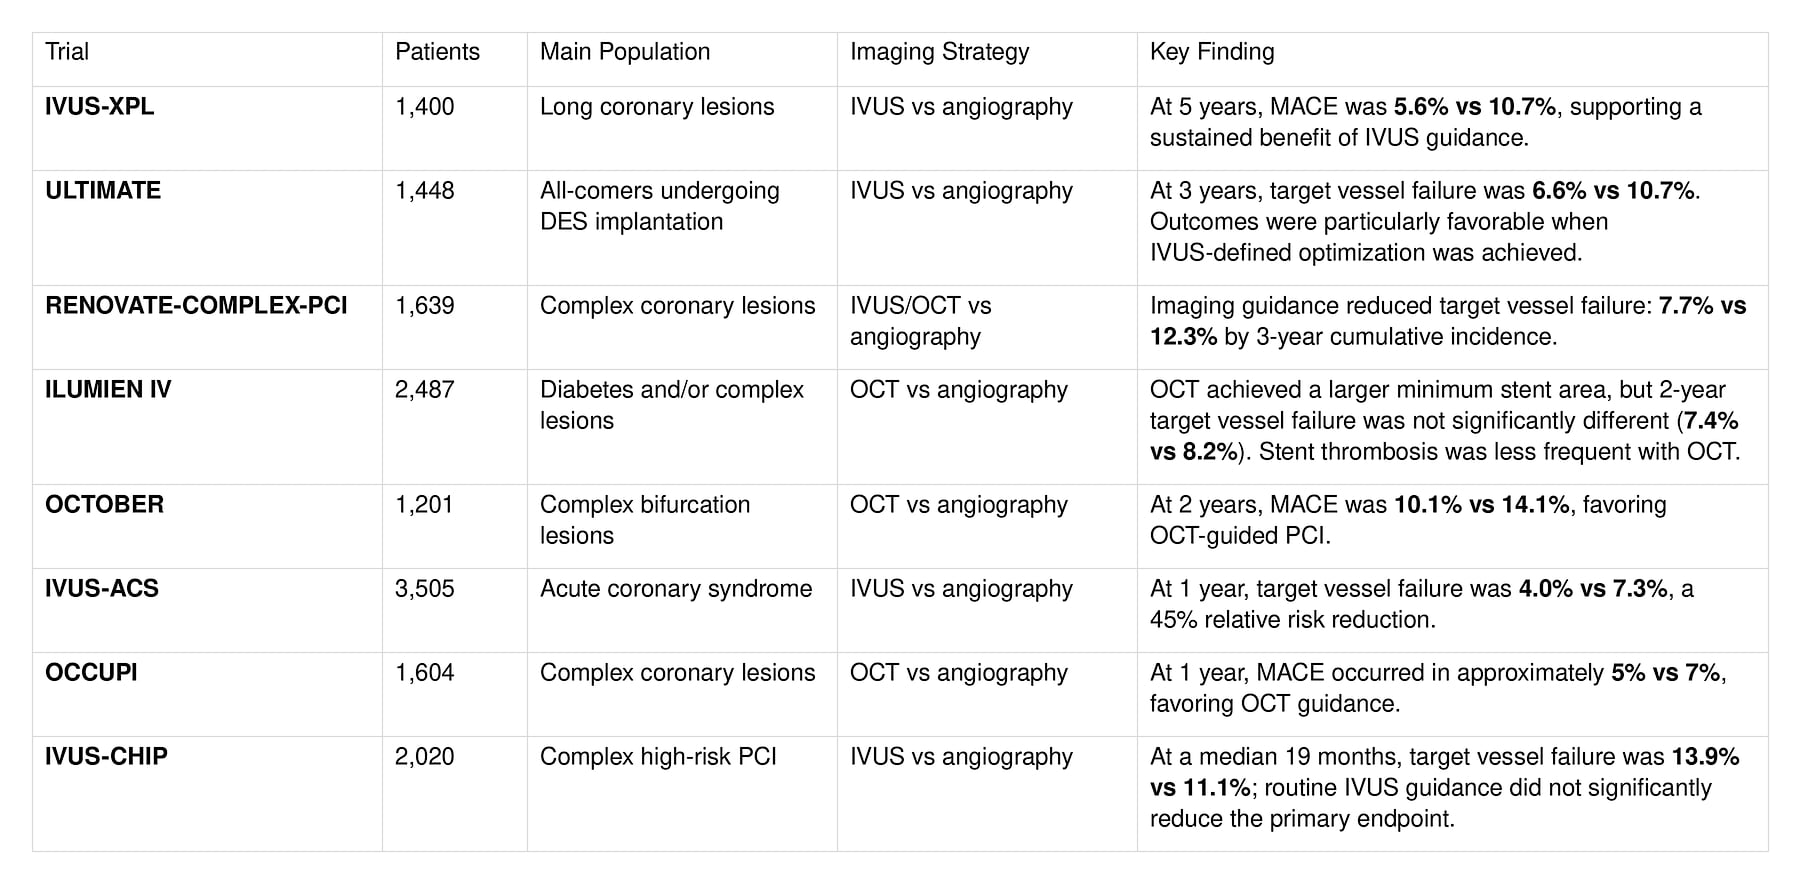
IVUS-ACS provides strong randomized evidence for IVUS-guided PCI in patients with acute coronary syndrome. At 1 year, IVUS guidance reduced target vessel failure from 7.3% to 4.0%, with the difference driven by reductions in target-vessel myocardial infarction and revascularization.
Beyond stent optimization, intracoronary imaging can also provide information about culprit-lesion morphology that may not be apparent on angiography alone.
Long Lesion
Long lesions are among the best-established settings for imaging-guided PCI.
In IVUS-XPL, patients requiring an implanted stent length of at least 28 mm experienced sustained clinical benefit from IVUS guidance through 5 years.
Imaging can help determine true vessel size, select appropriate landing zones, evaluate plaque distribution, and confirm that the diseased segment has been adequately covered.
Bifurcation Lesions
Bifurcation PCI presents additional technical challenges, including side-branch access, stent deformation, incomplete expansion, and ostial coverage.
In OCTOBER, OCT-guided PCI significantly reduced 2-year MACE in patients with complex bifurcation lesions.
High-resolution imaging can be particularly useful for assessing stent configuration and identifying technical issues that may be difficult to appreciate on angiography alone.
Left Main and Calcified Lesions
Intracoronary imaging can provide valuable anatomical information during left main PCI and in severely calcified lesions, where angiography may not accurately define vessel dimensions or calcium morphology.
However, clinical outcome data are not uniformly positive. For example, the 2026 OPTIMAL trial did not demonstrate superiority of routine IVUS guidance over angiography guidance in unprotected left main PCI.
This reinforces a broader principle: the value of imaging depends not only on where it is used, but also on how it is incorporated into the PCI strategy.
In calcified disease, OCT can characterize calcium thickness, arc, and fracture, while IVUS offers deeper penetration and can support vessel sizing even when calcification is extensive.
Imaging Alone Is Not Enough: Optimization Matters
The original article highlights four important mechanisms associated with stent failure: underexpansion, edge dissection, malapposition, and geographic miss.
The randomized evidence suggests that intracoronary imaging is most useful when incorporated into a structured workflow:
- Before stenting: plan the procedure. Imaging can help assess vessel size, plaque distribution, calcification, thrombus, landing zones, and appropriate stent dimensions.
- During PCI: guide complex decisions. This is especially valuable in bifurcation procedures and after lesion preparation, when imaging can identify technical problems and guide the next procedural step.
- After stenting: assess and optimize the final result. The operator should evaluate stent expansion, apposition, edge complications, and completeness of lesion coverage, then correct clinically relevant abnormalities when appropriate.
Optimization criteria differ between trials, vessels, and imaging modalities. For that reason, a single minimum stent area cutoff should not be treated as a universal target for every patient.
The more important principle is straightforward:
When imaging identifies a correctable problem, the information should be used to improve the PCI result.
IVUS or OCT: Which One Should You Choose?
Both IVUS and OCT are established modalities for PCI guidance. In the randomized OCTIVUS trial, OCT-guided PCI was noninferior to IVUS-guided PCI for the 1-year composite clinical endpoint, supporting the use of either modality when appropriately selected.
Their technical strengths, however, are different.
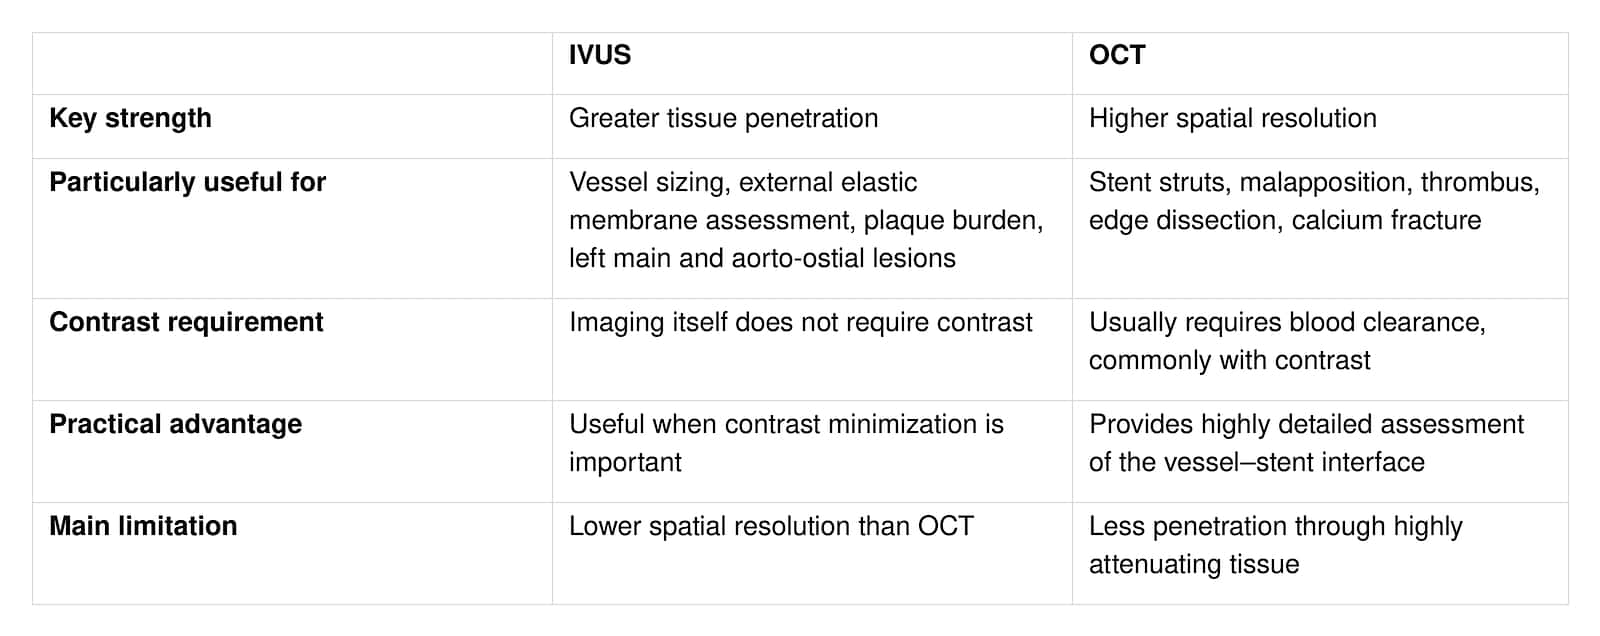
The practical question is therefore not simply “Which technology is better?”
It is:
“Which modality provides the information needed for this lesion, this patient, and this procedure?”
Lesion morphology, renal function, vessel location, the purpose of imaging, equipment availability, and operator experience should all influence the choice.
What Comes Next?
The next phase of intracoronary imaging is likely to focus on making imaging more standardized, easier to interpret, and more actionable.
AI-assisted analysis may help automate lumen measurements and improve recognition of calcium and plaque characteristics. Integration of physiological assessment with intracoronary imaging could bring anatomical and functional information into the same procedural workflow.
Another emerging direction is the combination of preprocedural coronary CT angiography with intraprocedural IVUS or OCT, creating a more continuous pathway from PCI planning to final stent optimization.
The Takeaway
Intracoronary imaging provides information that angiography alone may not reliably show—from true vessel dimensions and plaque distribution to calcium morphology, stent expansion, apposition, edge injury, and incomplete lesion coverage.


 IPv6 network supported
